What Is the Serum Anion Gap?
The serum anion gap is a derived value used in serum chemistry to analyze acid-base disorders, especially metabolic acidosis. It comes from a standard electrolyte panel and shows the balance between major measured serum electrolytes such as sodium, chloride, and bicarbonate. Because blood contains other positively and negatively charged particles that are not directly measured, the anion gap helps estimate the presence of unmeasured anions.
In simple terms, the serum anion gap is a indicator of anion concentration differences in the blood. A above-normal value usually suggests that acids or acid byproducts are accumulating. That is why the serum anion gap is a helpful diagnostic tool during laboratory assessment of patients with unexplained acidosis, shock, poisoning, or kidney dysfunction.
The classic formula is:
Anion gap = Sodium − (Chloride + Bicarbonate)
Some clinicians also include potassium in the calculation, but the most commonly used version excludes it because potassium contributes relatively little to the result. A normal serum anion gap often falls within a modest range, but the exact normal range depends on the laboratory method used and whether potassium is included.
The serum anion gap is closely tied to acid-base balance and electrolyte balance. When bicarbonate drops because it is being consumed by acids, the gap can rise if the lost bicarbonate is replaced by unmeasured acids. This makes the serum anion gap especially useful in identifying the underlying type of metabolic acidosis.
What Is the Urine Anion Gap?
The urinary anion gap is a distinct formula based on urinary electrolytes. Instead of assessing the blood directly, it helps estimate how well the kidneys are responding to acid loads by evaluating urinary acid excretion indirectly. It is usually calculated from sodium in urine, potassium in urine, and chloride in urine.
The usual formula is:
Urine anion gap = Urine sodium + Urine potassium − Urine chloride
This value is frequently used as a surrogate indicator for ammonium excretion, which is a primary way the kidneys clear acid. When urine chloride is greater compared with urine sodium and potassium, the urine anion gap tends to be negative, suggesting increased ammonium excretion. When the gap is above zero, it can suggest impaired renal acid excretion.
In contrast to the serum anion gap, the urine anion gap is not primarily about identifying unmeasured anions in blood. Instead, it is a method for evaluating renal handling of acid and evaluating whether the kidneys are appropriately adapting in the presence of non-anion gap metabolic acidosis.
The urinary anion gap can be particularly useful when clinicians need to differentiate whether a metabolic acidosis is due to a renal problem or to extrarenal losses such as gastrointestinal bicarbonate loss. In this context, the urine anion gap gives indirect insight into ammonium production, kidney function, and overall acid excretion.
Serum Anion Gap vs Kidney Anion Gap: Key Differences
Even though both measures use the term “anion gap,” they answer different medical questions. The serum anion gap focuses on the blood and is most useful for evaluating metabolic acidosis caused by added acids. The urine anion gap looks on the kidneys and is especially helpful for evaluating whether the kidneys are excreting acid effectively.
The main difference is the area being assessed. The serum anion gap indicates electrolyte balance in the bloodstream and helps identify excess acid or loss of bicarbonate substituted by other anions. The urine anion gap reflects urinary electrolytes and helps estimate renal ammonium excretion, which is central to the kidney’s response to acid retention.
In clinical practice, the serum anion gap is often the first test used when someone has acid-base abnormalities. If the serum gap is increased, clinicians think about causes such as lactic acidosis, ketoacidosis, or toxic alcohols. If the serum anion gap is not elevated but acidosis is still present, the problem may be a non-anion gap metabolic acidosis, and the urine anion gap may help decide whether the issue is renal or extrarenal.
Below is a practical way to think about the difference:
- Serum anion gap: reveals abnormal acids in blood and helps with acid-base interpretation. Urine anion gap: estimates kidney acid excretion and helps assess ammonium excretion. Serum test: relies on sodium, chloride, and bicarbonate from the electrolyte panel. Urine test: relies on urine sodium, urine potassium, and urine chloride.
Both are useful in clinical interpretation, but they are used for distinct parts of the website differential diagnosis. The serum anion gap asks, “What acids NAGMA causes are present in the blood?” The urine anion gap asks, “How is the kidney responding?”
How the Anion Gap Calculator Works
An anion gap calculator automates the core math used in clinical practice and can reduce errors during rapid review. The calculator typically uses the anion gap formula based on serum sodium, chloride, and bicarbonate. Some versions also offer potassium-inclusive calculations and present a corrected anion gap when albumin is low.
Why does albumin matter? Albumin is a primary unmeasured anion in the blood. When albumin decreases, the serum anion gap can look falsely low or normal even if significant acid is present. That is why a corrected value is often more revealing than the raw number alone.
A common correction approach includes a set amount to the measured anion gap for each decrease in albumin below normal. The exact adjustment can vary by institution, but the concept is the same: low albumin can mask a real gap. A corrected anion gap strengthens acid-base interpretation and helps prevent missed diagnoses.
Using the calculator effectively requires the right inputs from the electrolyte panel. For serum calculations, that means sodium, chloride, bicarbonate, and sometimes albumin. For urine calculations, it means urine sodium, urine potassium, and urine chloride. Because results can vary by lab reference standards, the normal range should always be interpreted alongside the patient’s clinical picture and the local laboratory method.
The most important limitation is that a calculator provides a number, not a diagnosis. The value must be interpreted in context with symptoms, blood gas data, kidney function, and other laboratory values. Used correctly, an anion gap calculator is a practical diagnostic tool for day-to-day laboratory assessment.
When to Consider Serum Anion Gap
The serum anion gap is especially helpful when there is suspicion of high anion gap metabolic acidosis. This is the classic setting in which acids collect in the blood and deplete bicarbonate, leaving behind excess unmeasured anions. Common causes include lactic acidosis, ketoacidosis, and toxic alcohols.
In lactic acidosis, tissue hypoperfusion, sepsis, seizures, or severe illness can increase lactate production and overwhelm normal buffering systems. In ketoacidosis, the body produces ketone acids in conditions such as diabetes, starvation, or alcohol-related illness. In toxic alcohols exposure, metabolites such as formate or glycolate can drive a marked increase in the serum anion gap.
The serum anion gap is also important when the cause of acidosis is not obvious. A normal bicarbonate level does not always rule out acid-base problems, especially when mixed disorders are present. A rising gap may be an early sign of worsening illness before other changes become obvious. In this sense, the serum anion gap provides a useful window into acid-base disorders and the balance between measured and unmeasured ions.
Another common use is tracking the anion gap over time. If treatment is effective, the gap should often fall as the underlying cause is addressed. That can help clinicians assess response during ongoing management of acidosis, shock, intoxication, or renal impairment.
When to Employ Urine Anion Gap
The urine anion gap is particularly valuable in evaluating non-anion gap metabolic acidosis, especially when the question is whether the kidneys are functioning appropriately. This is where renal tubular acidosis becomes a important factor. In renal tubular acidosis, the kidneys do not acidify urine normally, leading to poor acid excretion despite continued acid load.
Because the urine anion gap estimates ammonium excretion, it can help differentiate renal from nonrenal causes of non-anion gap metabolic acidosis. If ammonium excretion is high, the kidneys are responding appropriately, which argues against a primary kidney acidification problem. If ammonium excretion is low, the problem may be related to kidney disease or tubular dysfunction.
This test is most useful when gastrointestinal bicarbonate loss is possible. For example, in diarrhea, the body loses bicarbonate from the gut, causing non-anion gap metabolic acidosis. In that scenario, the kidneys should increase ammonium production and urine chloride excretion, often producing a negative urine anion gap. That pattern supports intact renal compensation.
In contrast, a positive urine anion gap in a patient with acidosis may suggest the kidneys are not excreting acid effectively. That finding can indicate a diagnosis of renal tubular dysfunction, chronic interstitial damage, or other forms of kidney disease. The urine anion gap therefore plays a key role in assessing renal handling of acid and the body’s ability to maintain acid-base balance.
How to Read Results in Clinical Practice
Clinical reading starts with recognizing whether the problem is mainly in blood chemistry, urine chemistry, or both. The serum anion gap and urine anion gap are not equivalent; each provides different information to the differential diagnosis. Reliable interpretation requires the full picture, including symptoms, blood gas data, and the broader electrolyte disorders pattern.
A high serum anion gap usually suggests a build-up of unaccounted-for acids. That may suggest diagnoses like lactic acidosis, ketoacidosis, toxic alcohols, or advanced renal failure. A normal serum anion gap with acidosis suggests a different path, often non-anion gap metabolic acidosis, where bicarbonate is lost and replaced by chloride.
The urine anion gap offers another layer of interpretation. A favorable urine anion gap often implies effective ammonium excretion, which is common in diarrhea-related acidosis. A elevated urine anion gap can indicate reduced renal acid excretion, which may be seen in renal tubular acidosis or other forms of kidney disease.
Lab results should never be read in isolation. Albumin, potassium, sodium, bicarbonate, chloride, creatinine, and blood gas measurements all influence interpretation. A patient with hypoalbuminemia may have a deceptively normal serum anion gap. A patient with severe illness may have mixed acid-base disorders that obscure the expected pattern. This is why the anion gap should be viewed as one part of a broader laboratory assessment rather than a stand-alone answer.
Typical Reasons of Atypical Anion Gap Values
Various conditions can affect the serum anion gap, the urine anion gap, or the two. Among the most frequent causes of a falsely low or deceptively normal serum anion gap is hypoalbuminemia. Because albumin is a important unmeasured anion, low levels lower the apparent gap and can mask a clinically important metabolic disturbance.
Chronic kidney disease can also change results. In advanced disease, acid excretion may decrease, and the serum anion gap may rise as retained acids accumulate. At the same time, kidney dysfunction can impair ammonium production and lead to abnormal urine anion gap findings. This is why kidney function is central to both serum and urine interpretation.
Diarrhea is a classic cause of non-anion gap metabolic acidosis because it causes bicarbonate loss from the gut. In that setting, serum bicarbonate falls, but the serum anion gap may stay normal unless another acid load is present. The urine anion gap may become negative if the kidneys respond as expected by increasing ammonium excretion.
Sepsis often causes elevated lactate and therefore a high serum anion gap. In severe cases, blood flow abnormalities, organ dysfunction, and altered buffering systems can create complex acid-base patterns. Sepsis can therefore produce high anion gap metabolic acidosis, mixed disorders, or both, making serial laboratory assessment necessary.
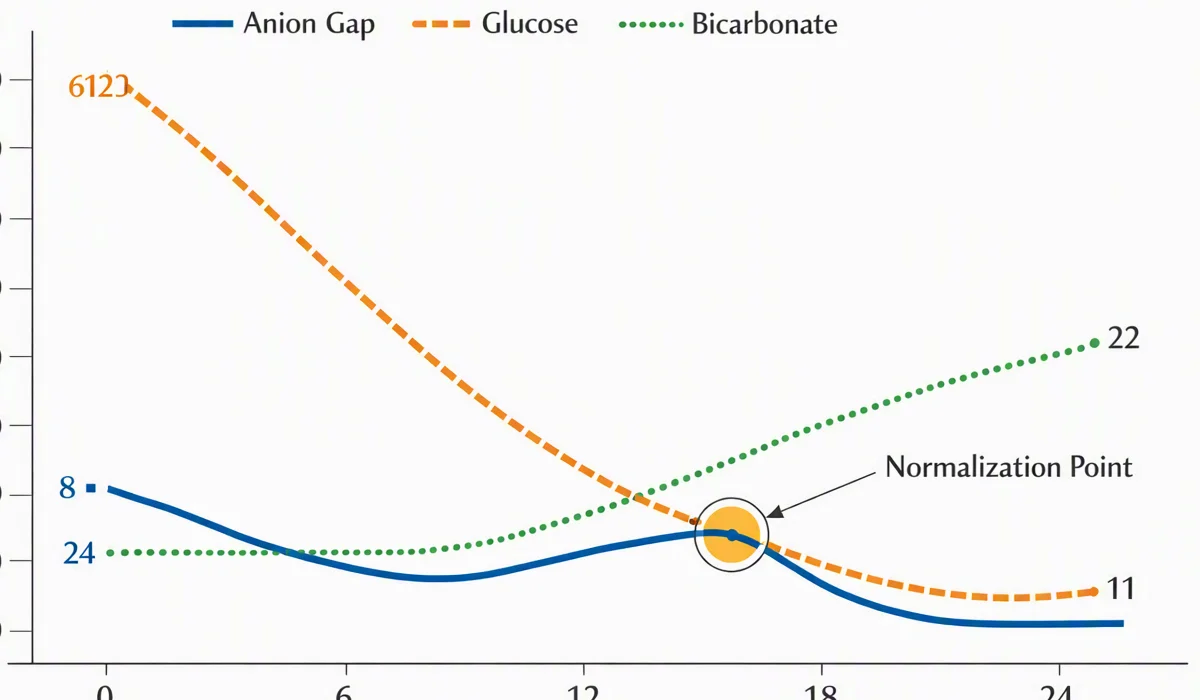
Other contributors to abnormal values include medication effects, dehydration, vomiting, urinary losses, and changes in potassium or chloride handling. Because acid-base disturbances often overlap, the clinician should use the serum anion gap and urine anion gap as part of a structured approach rather than as isolated numbers.
Frequently Asked Questions
What is the difference between serum anion gap and urine anion gap?
The serum anion gap measures the difference between major measured blood electrolytes, mainly sodium, chloride, and bicarbonate, to help detect unmeasured anions and evaluate acid-base disorders. The urine anion gap uses urine sodium, urine potassium, and urine chloride to estimate ammonium excretion and assess how well the kidneys are responding to acidosis.
How do you calculate serum anion gap with an Anion Gap Calculator?
An anion gap calculator usually follows the formula sodium minus the sum of chloride and bicarbonate. Some calculators also include potassium or provide a corrected anion gap when albumin is low. You provide the laboratory values, and the tool runs the calculation to aid clinical interpretation.
When is urine anion gap more useful than serum anion gap?
The urine anion gap is more helpful when evaluating non-anion gap metabolic acidosis, especially if the question is whether the kidneys are excreting acid properly. It is particularly important in suspected renal tubular acidosis or when trying to distinguish renal causes from bicarbonate loss due to diarrhea.
What does a high serum anion gap mean?
A high serum anion gap usually indicates there are extra unmeasured acids in the blood. Common causes include lactic acidosis, ketoacidosis, and toxic alcohols. It can also occur with advanced chronic kidney disease or other conditions that promote acid retention.
Can a normal anion gap still indicate a serious acid-base disorder?
Yes. A normal anion gap does not rule out a serious problem. It may reflect non-anion gap metabolic acidosis, mixed acid-base disorders, or a masked disturbance from hypoalbuminemia. That is why the full clinical context, including albumin, bicarbonate, potassium, and other laboratory values, is necessary for accurate clinical interpretation.